Tag Archives: Clinical Cases

Why a Restoration Must Follow the Approved Wax-Up

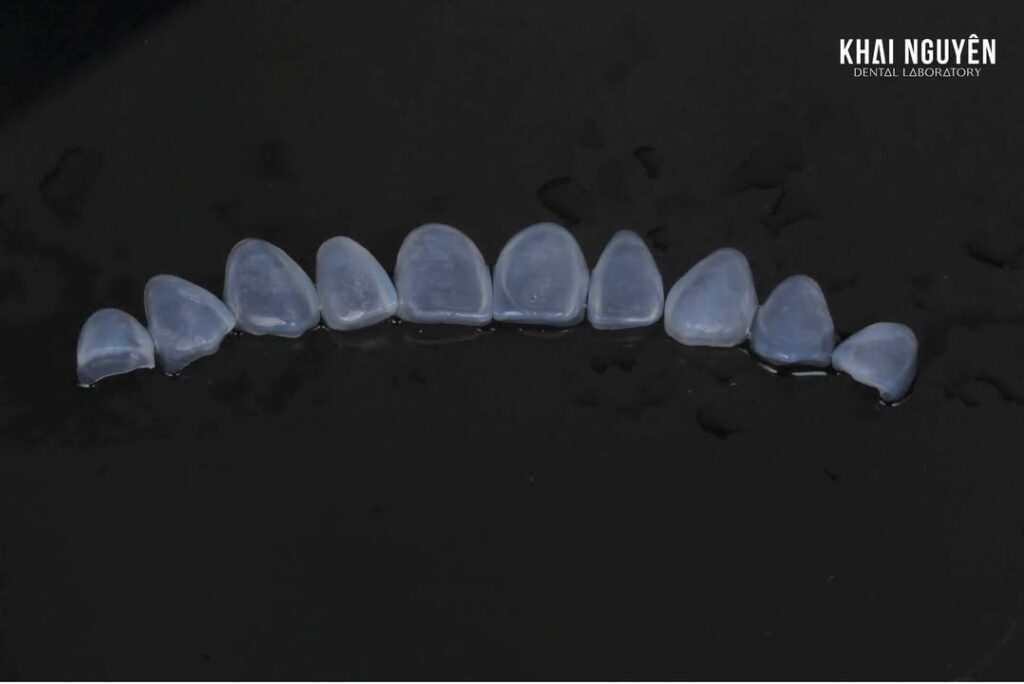
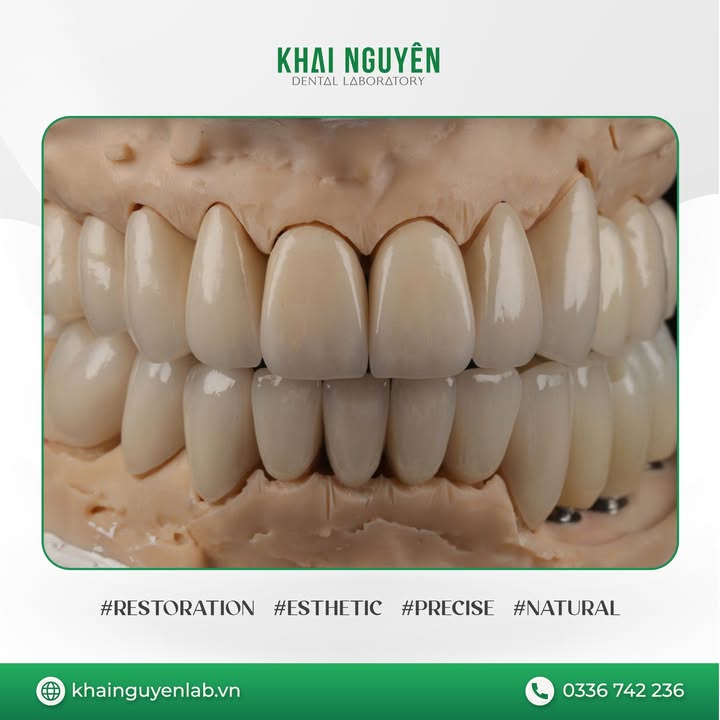
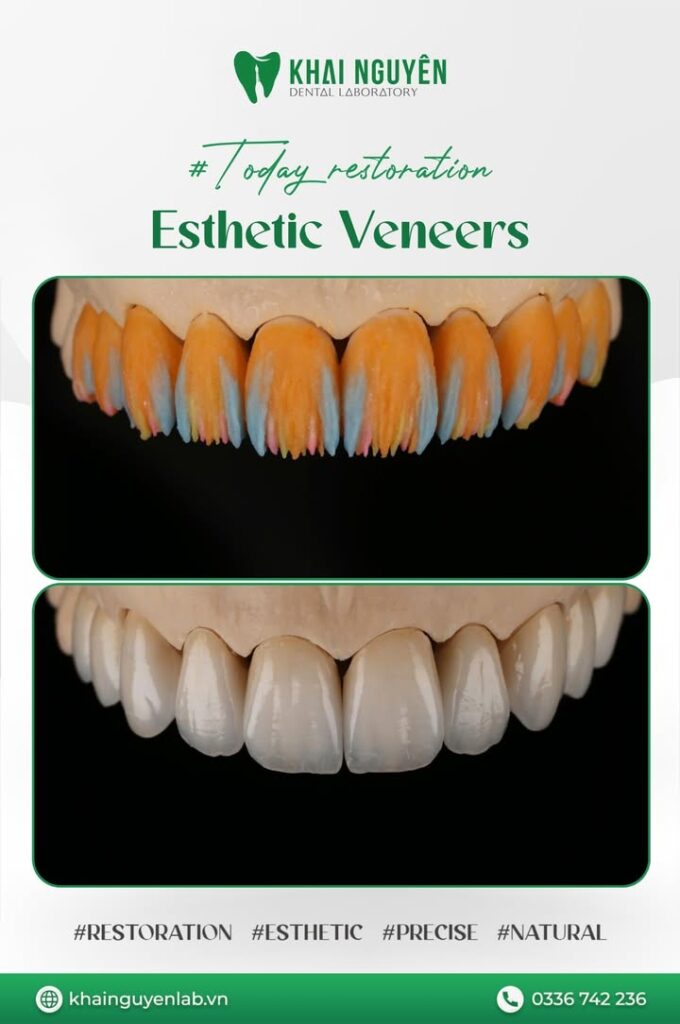
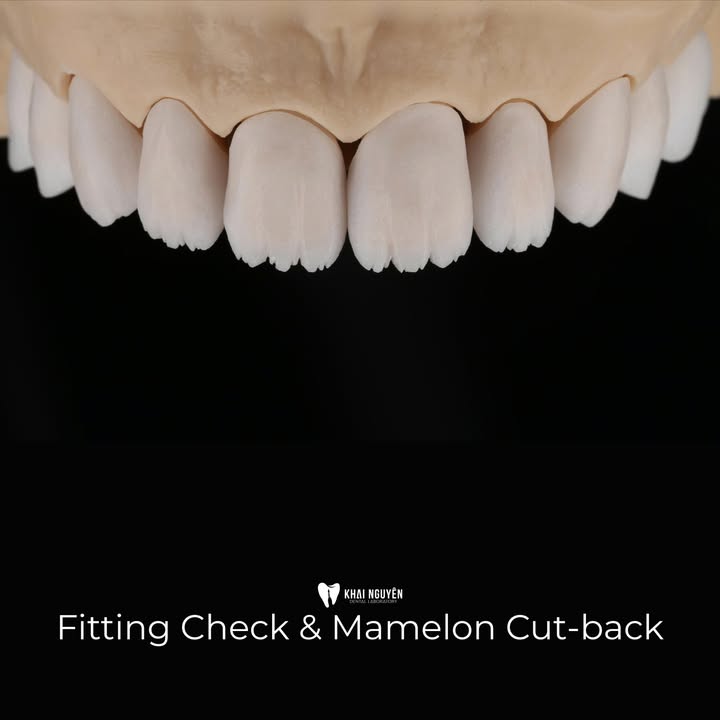
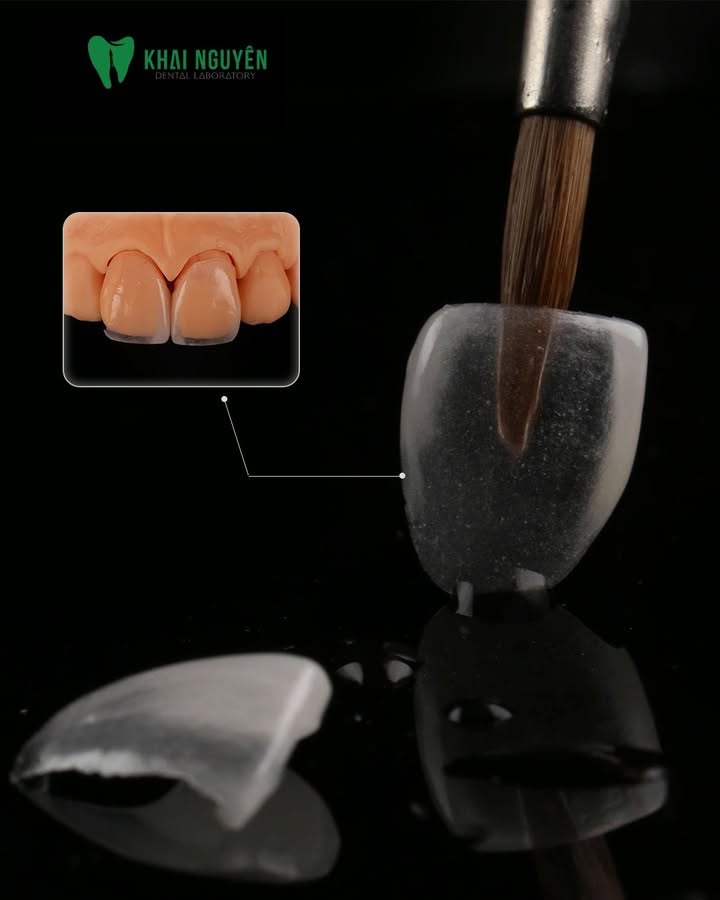
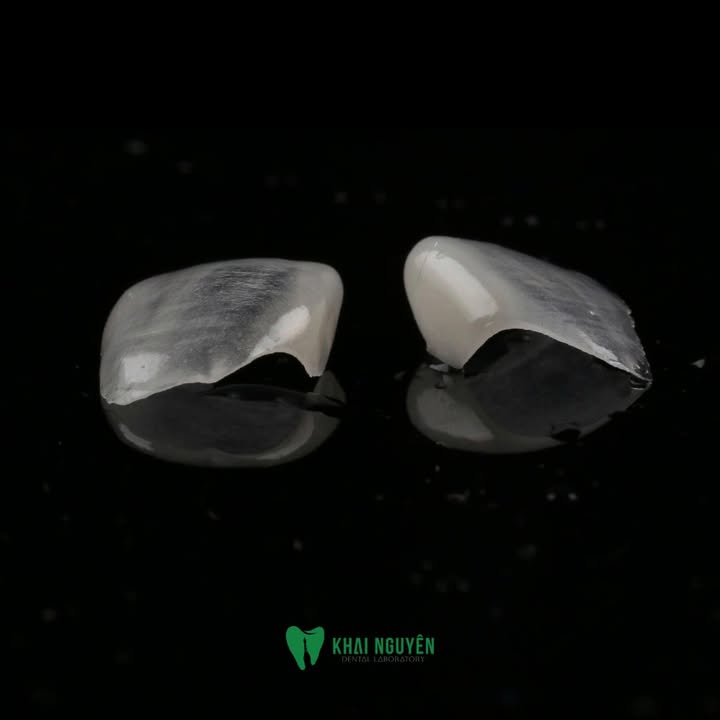
Veneer 10 răng hàm trên bằng Amber Mill, màu 1M1 đến 1M2

A ten-unit upper veneer case in Amber Mill, shade 1M1 to 1M2. What makes this case worth recording is that the finished restoration follows the wax-up design exactly.

Case parameters

  • Restoration: ten upper veneers
  • Material: Amber Mill
  • Shade: 1M1 to 1M2
Veneer 10 răng hàm trên bằng Amber Mill, màu 1M1 đến 1M2
Case image by Khai Nguyen Dental Lab.

Why following the wax-up matters

In an esthetic workflow, the wax-up is the design the clinician and patient agree on before any tooth is prepared. If the final restoration drifts from it, everything that was agreed loses its force: the patient expected one shape and receives another.

In a CAD/CAM workflow the wax-up is digitised and becomes the reference for every step that follows. The restoration is milled from that same dataset, so the difference between the approved design and the delivered result is close to zero.

The practical benefit

When the finished work reproduces the original design, quality control becomes straightforward: compare the restoration against the wax-up rather than judging it subjectively. Chair time at try-in also shortens, because the form was approved in advance.

What clinicians can use from this

On a multi-unit esthetic case, time invested in the wax-up and mock-up early saves more time later. Sending the lab a wax-up the patient has already approved, together with intraoral mock-up photographs, is the fastest route to a restoration that meets expectations.

See our esthetic restorations range, or contact our team.

Written for dentists and technicians. Khai Nguyen Dental Lab manufactures to clinical prescription only and does not sell directly to patients.

See the full case record with the spec table, image source and step-by-step workflow: Case Study: Ten Amber Mill Veneers in 1M1–1M2 Following the Approved Wax-Up.
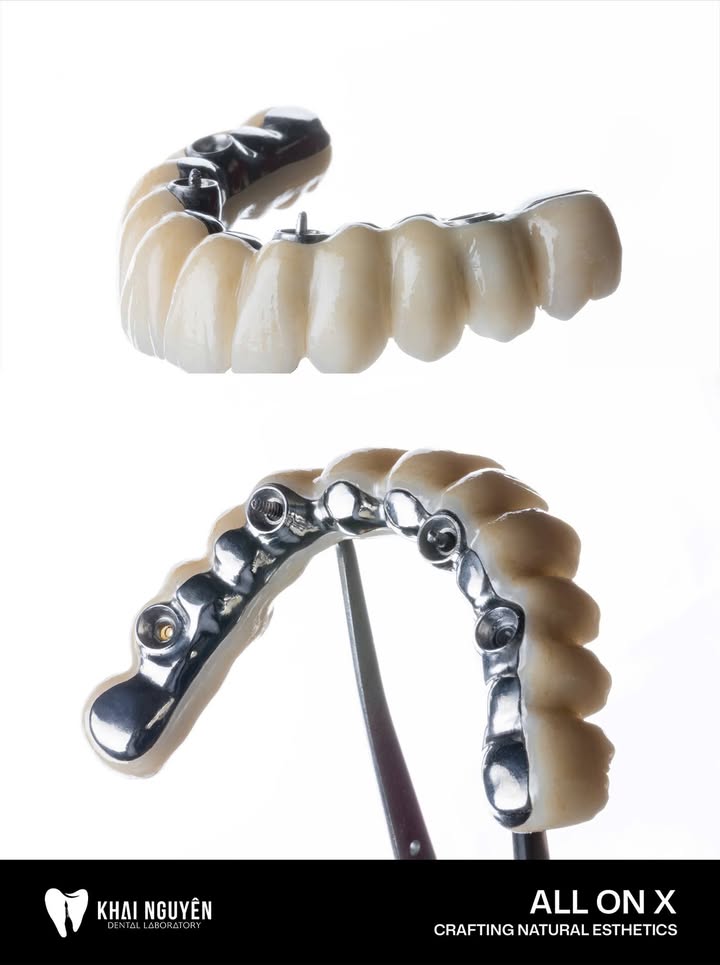
Bar-Supported Implant Restorations and Passive Fit

Phục hình implant trên thanh bar

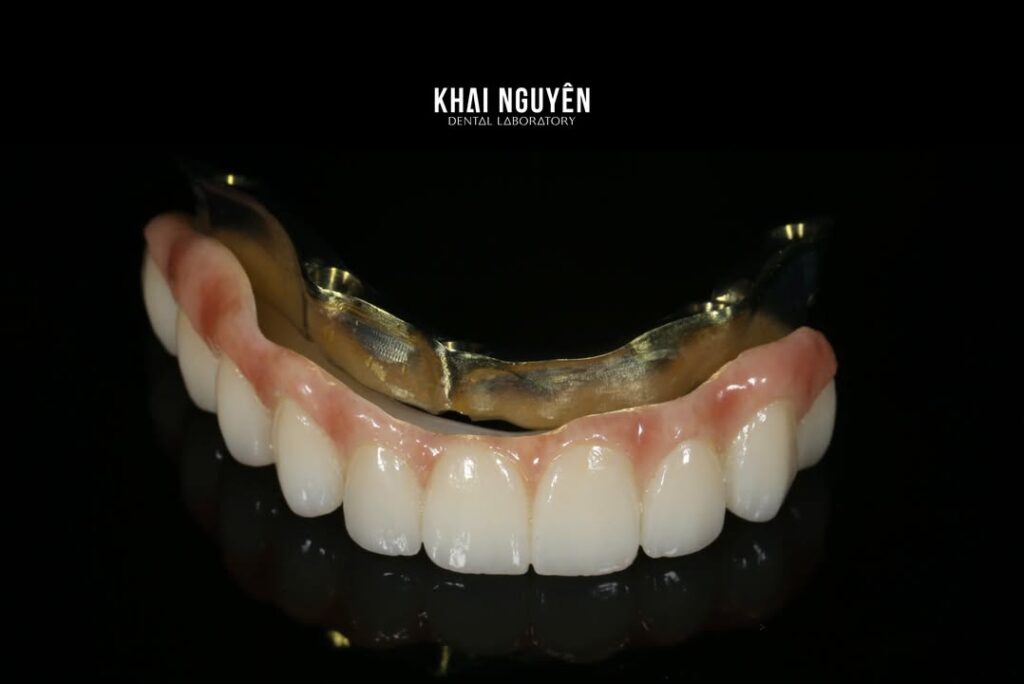
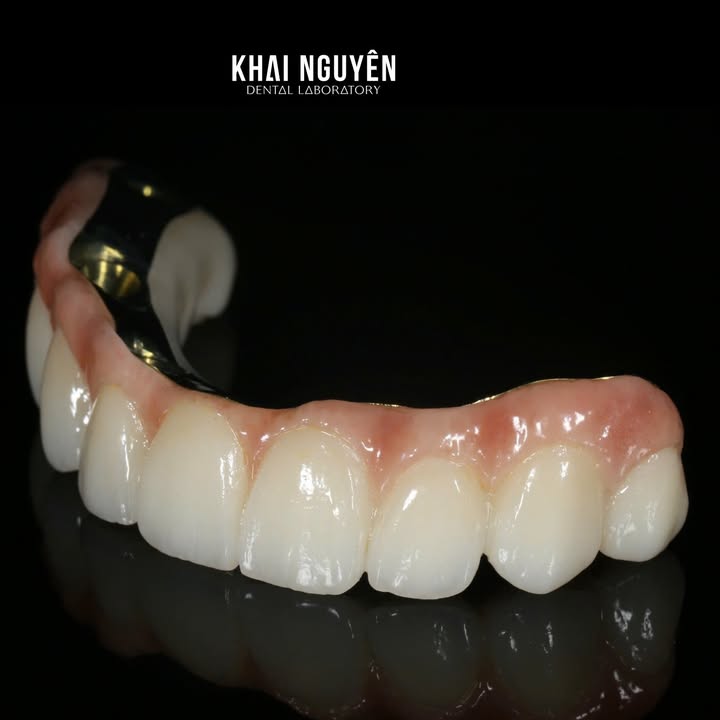
Bar-supported implant restorations demand close coordination between clinic and laboratory, and precision at every step.

Why a bar is unforgiving on tolerance

On a natural tooth, the periodontal ligament allows several tens of microns of movement, enough to absorb part of a restoration’s discrepancy. An implant integrates directly with bone and has almost none of that capacity.

A bar joining several implants therefore has to seat passively: place it and it sits, without tightening screws to draw it into position. If it has to be pulled in, that residual load stays in the system and shows up later as a loosening screw, a fractured screw, or bone loss around the implant.

Phục hình implant trên thanh bar
Case image by Khai Nguyen Dental Lab.

Where the process is controlled

Accuracy on a bar case does not come from one step but from a chain: recording implant positions by impression or scan, transferring them to the model without distortion, fabricating the bar, then verifying fit before any esthetic work begins. An error at any stage carries into the next.

At Khai Nguyen these cases follow a workflow with a checkpoint at each stage, because catching a discrepancy at the bar stage costs far less than finding it after the ceramic is on.

What clinicians can use from this

On a bar case, the quality of the implant position record drives most of the result. With a conventional impression, splint the impression copings together. With a digital workflow, use scan bodies matched to the system and verify with a confirmation scan.

See implant restorations, or contact our team.

Written for dentists and technicians. Khai Nguyen Dental Lab manufactures to clinical prescription only and does not sell directly to patients.

A Ten-Unit Feldspathic Case and Enamel-Like Translucency

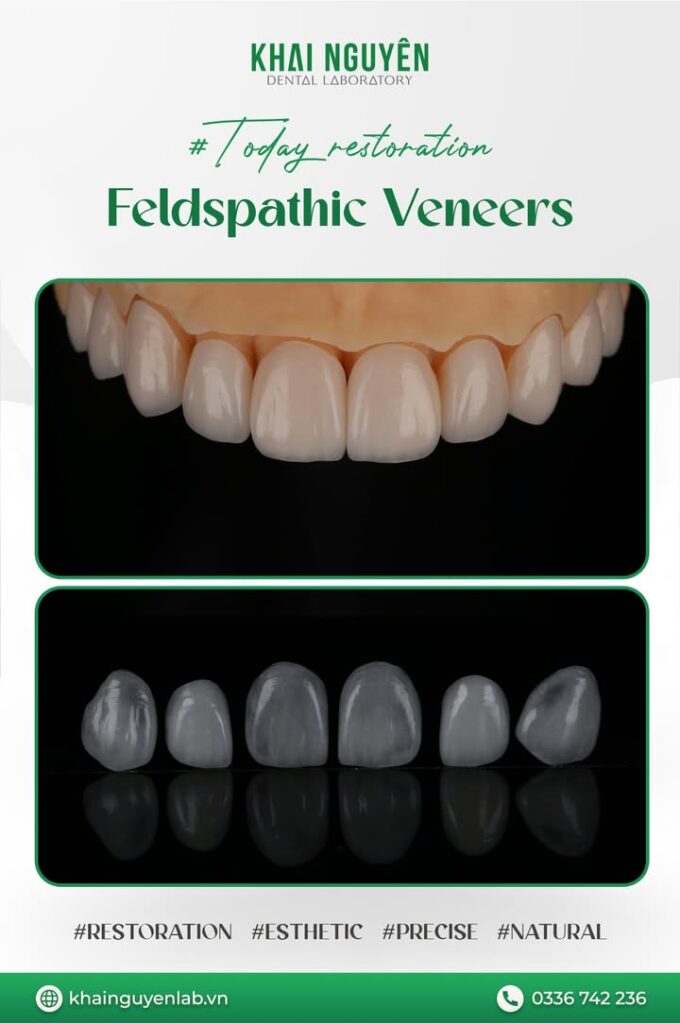
Ca feldspathic 10 răng, tái tạo hiệu ứng trong mờ như men răng thật

A ten-unit feldspathic case, which belongs to the most demanding esthetic group a laboratory receives.

Why ten units is harder than ten times one unit

A single feldspathic veneer is difficult because it has to match its neighbours. With ten units the problem inverts: there is no natural tooth left to match, but now the lab has to create deliberate difference between the teeth.

No two teeth in a natural dentition are identical. Central incisors are brighter and more translucent at the edge; lateral incisors are smaller and usually more translucent throughout; canines are more saturated with a pronounced facial convexity. Build all ten to one shade recipe and the result is perfectly uniform, and therefore reads as false.

Ca feldspathic 10 răng, tái tạo hiệu ứng trong mờ như men răng thật
Case image by Khai Nguyen Dental Lab.

The hardest part: translucency

Natural enamel is neither transparent nor opaque. It scatters light, producing a brighter incisal zone with a thin halo, and lets the dentine colour beneath show through cervically. In hand-layered ceramic that effect is built by stacking materials of differing opacity in the right order, and there is no way to correct it after firing.

What clinicians can use from this

For a multi-unit anterior case, send the lab natural smile photographs, not only retracted intraoral views. Smile line, tooth display in speech and the relationship with the lower lip are only visible in a portrait, and they determine the length and inclination of all ten units.

See feldspathic veneers, or contact our team.

Choosing between the two materials? See feldspathic or e.max veneers: how to choose.

Written for dentists and technicians. Khai Nguyen Dental Lab manufactures to clinical prescription only and does not sell directly to patients.

Full-Cutback on Multi Zirconia: Layering the Facial Surface

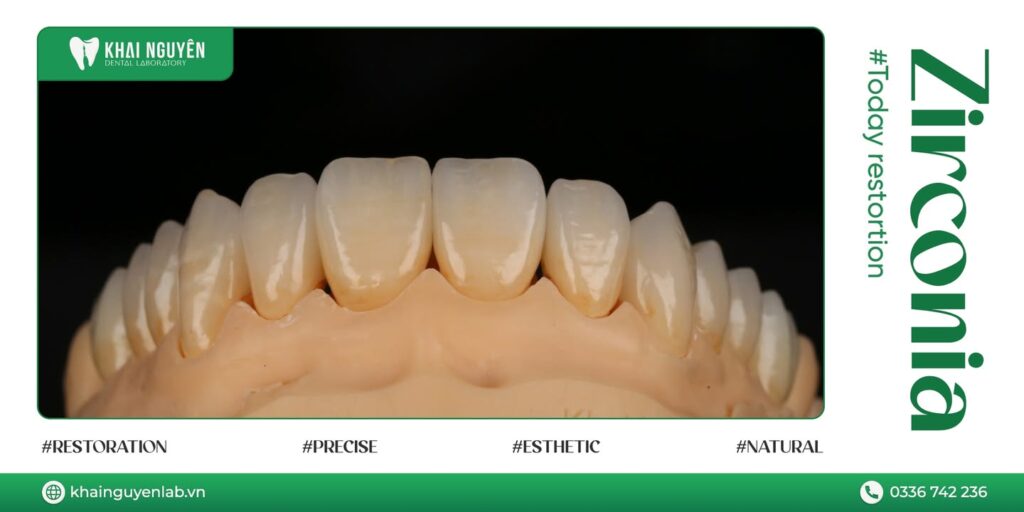
Phục hình Multi Zirconia kỹ thuật full-cutback đắp sứ mặt ngoài

A case using the full-cutback technique: a Multi Zirconia blank with the facial surface cut back and ceramic layered onto the reduced area.

What full-cutback is, and how it differs from monolithic

A monolithic zirconia restoration is milled from the blank, then stained and glazed on the surface. It is fast and strong, but the colour effect sits on the surface, so optical depth is limited.

In a full-cutback, the technician reduces the facial aspect of the zirconia framework and layers ceramic over that area. The interior of the tooth stays dense load-bearing zirconia while the visible surface becomes multi-layered ceramic with genuine depth.

Phục hình Multi Zirconia kỹ thuật full-cutback đắp sứ mặt ngoài
Case image by Khai Nguyen Dental Lab.

Why a multilayer blank

A multilayer blank already carries shade and translucency bands through its vertical axis. When the facial surface is cut back, the remaining core still holds the gradient from cervical to incisal, so the layered ceramic does not have to carry the whole colour effect and only adds the finest part of it.

The trade-off to know

Full-cutback delivers higher esthetics than monolithic, but layered facial ceramic is less durable than dense zirconia and needs sufficient space. In heavy load-bearing areas, or for a patient who brings a parafunctional habit, consider cutting back less, or keeping the posterior units monolithic.

What clinicians can use from this

When prescribing, state the priority plainly: maximum esthetics or maximum durability. The lab will then propose a full cutback, a partial cutback limited to the incisal third, or a monolithic result, depending on the restorative space and the patient’s functional habits.

See our zirconia range, or contact our team.

Written for dentists and technicians. Khai Nguyen Dental Lab manufactures to clinical prescription only and does not sell directly to patients.

Mixing Restoration Types in One Case: Two Challenges

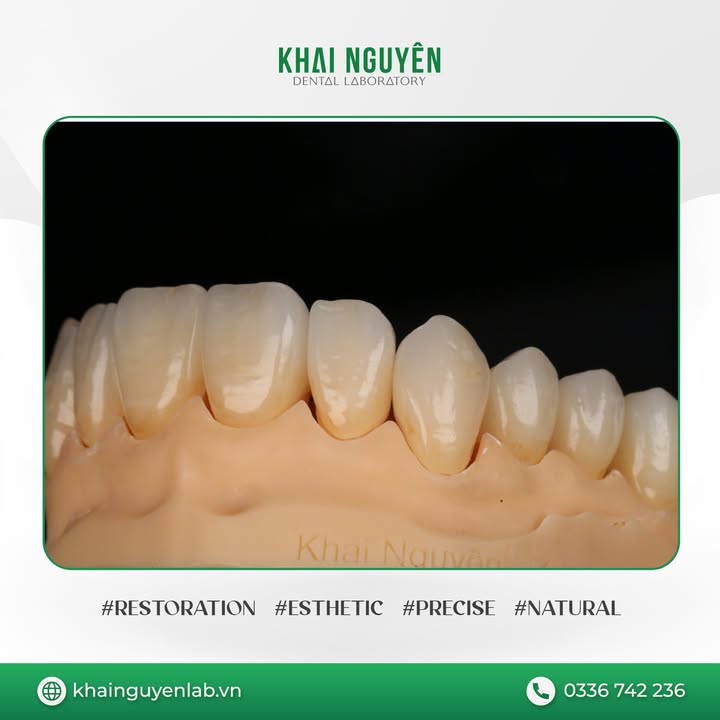
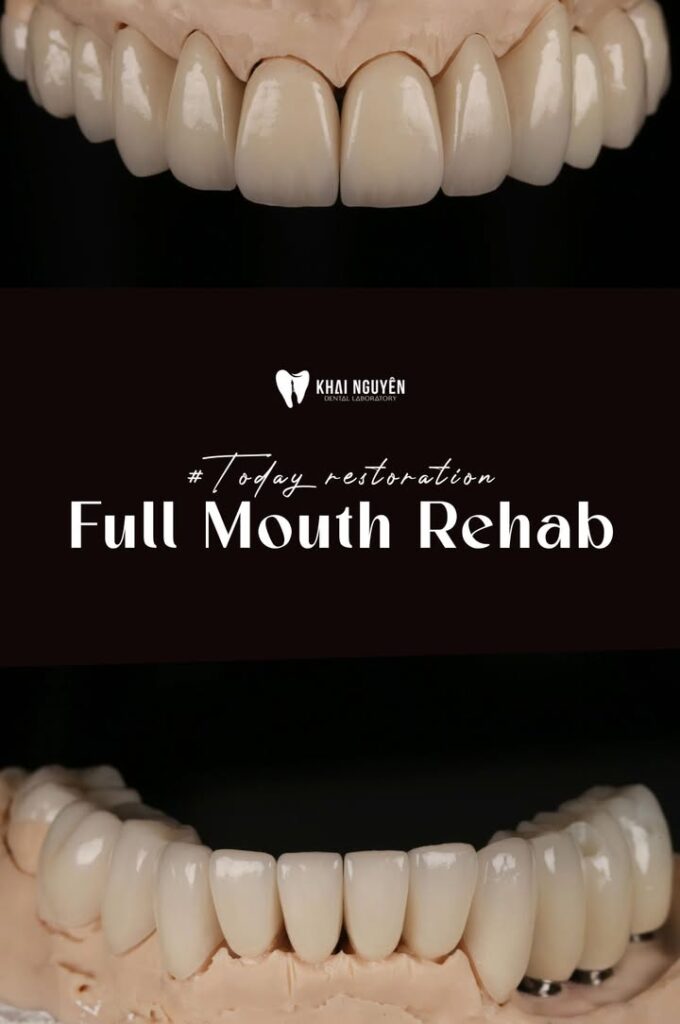
Ca nâng khớp toàn hàm kết hợp veneer, onlay, mão và phục hình trên implant

A full-mouth case with an increase in vertical dimension, recently completed at Khai Nguyen, combining veneers, onlays, ceramic crowns and implant-supported restorations in one plan.

Two challenges when a case mixes restoration types

Controlling the occlusion. Raising the vertical dimension changes the whole inter-arch relationship. Every group has to be built to the same occlusal plane and the same guidance, otherwise one group contacts early and another sits out of occlusion.

Keeping shade consistent across different restoration types. This part is routinely underestimated. Veneers are thin, so the preparation shade shows through strongly. Onlays are thicker occlusally. Crowns cover the whole preparation and can mask the substrate. Implant restorations have no natural preparation beneath them at all, only an abutment. Those four groups start from completely different backgrounds, and the result has to read as one set of teeth.

Ca nâng khớp toàn hàm kết hợp veneer, onlay, mão và phục hình trên implant
Case image by Khai Nguyen Dental Lab.

How the lab handles it

The case is planned as a whole rather than built group by group and assembled afterwards. The technician fixes the occlusal plane and the target shade for the entire arch first, then works backwards to the thickness and opacity each group needs so that all of them arrive at the same colour.

What clinicians can use from this

For a mixed case, three things should be settled before production: how much the bite is being raised, the actual preparation shade in each zone, and the target shade. A wax-up or mock-up the patient has already approved shortens try-in considerably.

See our restorations range, or contact our team.

Another bite-raising case: full-arch vertical dimension rehabilitation with 20 ZirCAD Prime crowns and LiSi overlays.

Written for dentists and technicians. Khai Nguyen Dental Lab manufactures to clinical prescription only and does not sell directly to patients.

See the full case record with the spec table, image source and step-by-step workflow: Full-Mouth Rehabilitation Combining Veneers, Onlays, Crowns and Implants: Occlusion Control and Shade Consistency.

An I-Bar Under Zirconia for Long-Span and Cantilever Bridges

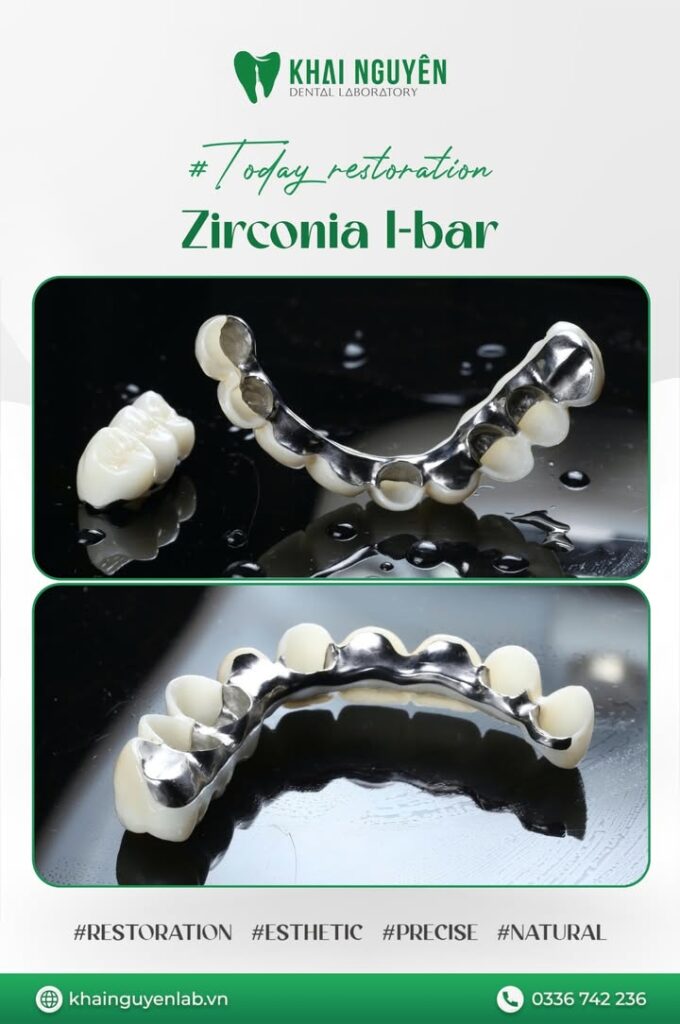
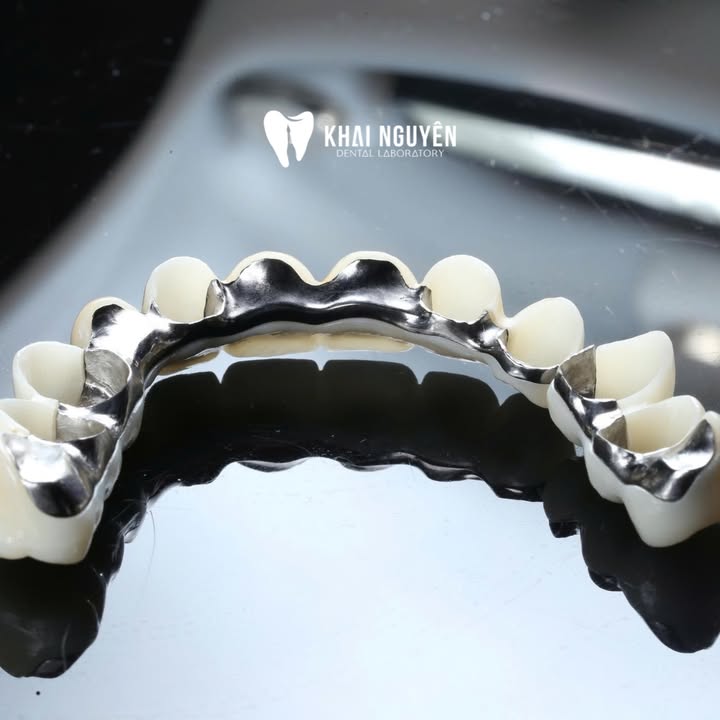
Khung I-bar kim loại kết hợp mão zirconia cho cầu dài

For restorations with a long span or a cantilever, where the restorative space allows it, an I-bar under zirconia is an option worth considering.

The problem with long spans and cantilevers

Deflection in a bridge span rises with the cube of the span length. Double the span and deflection increases roughly eightfold. With a cantilever, load also arrives off-axis on the abutment, which raises stress at the connector.

Zirconia on its own handles compression very well but is brittle under the tensile bending that occurs at connectors. That is why fractures in long-span bridges usually appear at the connector rather than mid-span.

Khung I-bar kim loại kết hợp mão zirconia cho cầu dài
Case image by Khai Nguyen Dental Lab.

How the I-bar addresses it

Three points make this solution worth considering:

  • Load bearing. The metal acts as a reinforcing framework, reducing the risk of fracture at the connector.
  • Stable esthetics. The zirconia facial surface masks the metal effectively and still meets esthetic requirements in conversation range.
  • An additional treatment option. It gives the clinician a further safe route when planning complex long-span or cantilever cases.

When it applies

The condition is sufficient restorative space. The metal framework needs a minimum thickness, and the zirconia facing needs its own. If the interocclusal space is tight, the trade-off between strength and esthetics has to be settled before production, not at the finishing stage.

What clinicians can use from this

When sending a long-span case, state the span length, whether there is a cantilever, and the measured interocclusal space. Those three figures are enough for the lab to advise whether monolithic zirconia is sufficient or a reinforcing framework is warranted.

See our materials and restorations range, or contact our team.

Written for dentists and technicians. Khai Nguyen Dental Lab manufactures to clinical prescription only and does not sell directly to patients.

The Four Stages That Decide a Pressed Veneer Case

Veneer GC LiSi Press hoàn thiện tại Khai Nguyên Dental Lab

A GC LiSi Press veneer case recently completed at Khai Nguyen. This note records the sequence of steps behind it.

Four stages that decide the result

Adjusting the coping for fit. Before shade enters the conversation, the restoration has to seat correctly on the preparation. This is settled at the framework stage, because any discrepancy left afterwards gets covered by ceramic and can no longer be corrected.

Hand layering. LiSi Press provides a good translucent base, but the shade transition and the liveliness of the incisal edge still have to be placed layer by layer by the technician.

Shaping the form. Form decides whether a veneer looks natural more than shade does. Length, outline, facial convexity and contact point position all have to suit the patient’s face and smile line.

Creating surface texture. Natural teeth are not flat. Fine horizontal ripples and vertical grooves scatter light instead of reflecting it as one bright patch. Skip this and the veneer will be evenly coloured yet still read as artificial.

Veneer GC LiSi Press hoàn thiện tại Khai Nguyên Dental Lab
Case image by Khai Nguyen Dental Lab.

What this shows

None of the four stages rescues a mistake from the one before it. A coping that does not seat makes good shade irrelevant; wrong form cannot be saved by texture. That is why the lab checks at each stage rather than only inspecting the finished unit.

What clinicians can use from this

On a high-esthetic case, ask the lab for photographs at the framework stage or before glazing. A few minutes reviewing an image then is far cheaper than one remake.

See GC LiSi Press, or our ceramic materials comparison.

Written for dentists and technicians. Khai Nguyen Dental Lab manufactures to clinical prescription only and does not sell directly to patients.

See the full case record with the spec table, image source and step-by-step workflow: Case Study: Ten GC Initial LiSi Press Veneers in BL2, Teeth 14 to 24.

Feldspathic Veneers on Teeth 11 and 21, Layered by Hand

Veneer feldspathic đắp tay cho răng 11 và 21

Two central incisors, two hand-layered feldspathic veneers. It sounds contained, and it is the most demanding esthetic group a laboratory takes on.

Why teeth 11 and 21 are difficult

On a full arch, the lab sets its own shade and form reference and applies it throughout. On 11 and 21 the reference is already there: the patient’s own 12 and 22. The two new veneers have to match them on base shade, incisal translucency, cervical saturation and the way the surface catches light.

There is a second factor. The central incisors sit at the middle of the smile and mirror each other. A few tenths of a millimetre of difference in length or axial inclination shows immediately, while the same deviation on a molar goes unnoticed.

Veneer feldspathic đắp tay cho răng 11 và 21
Case image by Khai Nguyen Dental Lab.

Why feldspathic, and why hand layering

Feldspathic ceramic produces the closest optical match to natural enamel and can be made very thin, which preserves tooth structure. In exchange it lacks the strength of lithium disilicate or zirconia and depends entirely on the quality of the bond.

Layering by hand lets the technician place opacity at the cervical, the transition through the body, and translucency with a halo effect at the incisal edge the way natural enamel behaves. That is the part a machine does not replace.

What clinicians can use from this

On a two-central case, the shade photographs matter more than the written shade. Take them with the shade tab in frame, before the teeth dehydrate, and add an angled view so the lab can read incisal translucency.

See feldspathic non-prep veneers, or contact our team.

Choosing between the two materials? See feldspathic or e.max veneers: how to choose.

Written for dentists and technicians. Khai Nguyen Dental Lab manufactures to clinical prescription only and does not sell directly to patients.

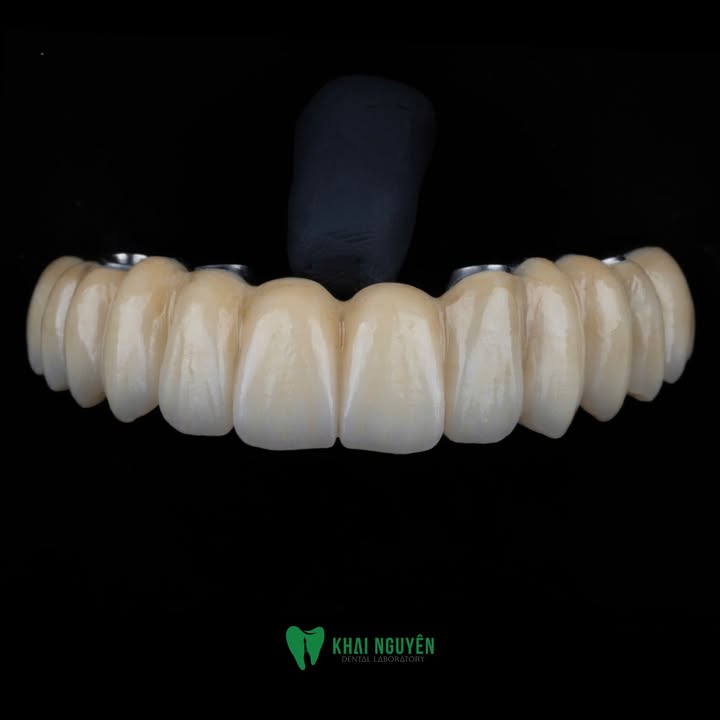
All-on-4 in FP1: Why the Tissue Surface Is Polished

Phục hình All-on-4 FP1 trên phôi zirconia màu A2

An All-on-4 case in the FP1 configuration, recently completed at Khai Nguyen on Aidite 3D Pro zirconia in shade A2.

How FP1 differs from the rest

In the classification of full-arch implant restorations, FP1 replaces the clinical crown only, not the gingiva. The restoration therefore has to terminate against the patient’s own soft tissue, which makes the ceramic-to-tissue interface the most important detail in the case.

In FP2 and FP3 designs, pink ceramic covers the transition zone. In FP1 there is nothing to hide behind. If the tissue surface is rough or has a microgap, plaque accumulates exactly where the patient finds it hardest to clean.

Phục hình All-on-4 FP1 trên phôi zirconia màu A2
Case image by Khai Nguyen Dental Lab.

Why the lab polishes the tissue surface so carefully

On FP1 cases our team polishes the tissue-contacting surface with particular care, for biological safety and to keep the restoration cleansable. Properly polished zirconia has a far lower surface roughness than a glazed-only surface, and that roughness directly affects how much plaque accumulates around the restoration over time.

None of this shows in a smile photograph, yet it largely decides how healthy that restoration still is several years later.

What clinicians can use from this

When planning an All-on-X case, agree the FP1, FP2 or FP3 route with the lab early, because the choice changes both the design and the amount of finishing work involved. Photographs of the healed soft tissue and information about the smile line let the lab decide where the restoration should terminate.

See implant bridges and crowns, or contact our team.

Written for dentists and technicians. Khai Nguyen Dental Lab manufactures to clinical prescription only and does not sell directly to patients.

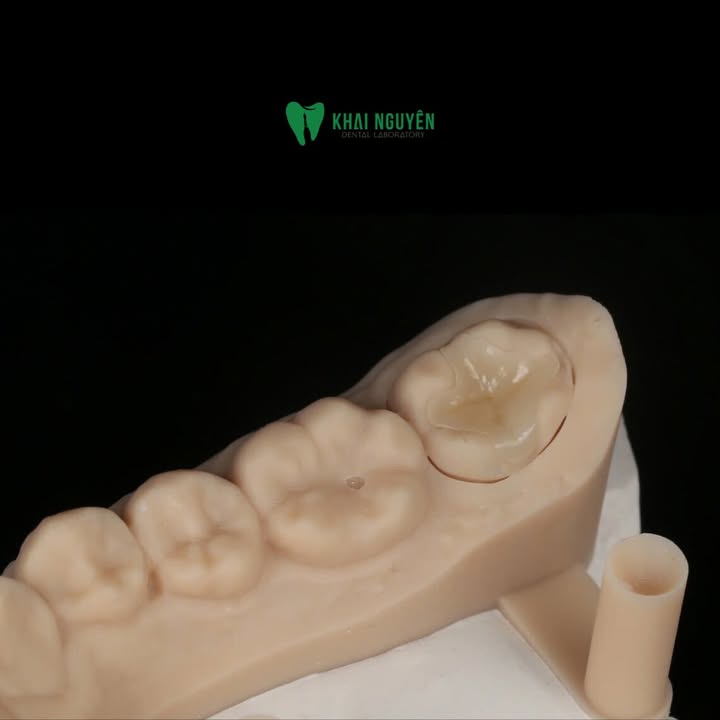
A Ceramic Inlay Case: Marginal Fit and Occlusal Anatomy

Inlay sứ đặt trên mẫu, kiểm tra độ khít sát và giải phẫu mặt nhai

Not every case is a full smile makeover. Every so often the bench comes back to a small restoration such as a single inlay, and this group has a difficulty of its own.

Why inlays and onlays are harder than they look

An inlay looks simple because it is one piece of ceramic. Being small is exactly what removes the margin for error. A crown wraps the preparation and has walls that can absorb a discrepancy; an inlay sits inside the cavity, so its finish line is exposed on the occlusal surface, where the patient’s tongue touches it every day and where food packs if the fit is not right.

Two requirements have to be met at once. First, marginal fit around the entire cavity outline, not at a few points. Second, occlusal anatomy that continues into the remaining tooth structure: grooves, marginal ridges and cusps have to follow the direction of that particular tooth rather than a standard shape pulled from a library.

Inlay sứ đặt trên mẫu, kiểm tra độ khít sát và giải phẫu mặt nhai
Case image by Khai Nguyen Dental Lab.

What the lab does

The technician starts by reading the cavity form the clinician prepared, then rebuilds the missing structure along the existing groove and cusp directions. When the ceramic seats cleanly and the junction almost disappears, it means both the preparation and the fabrication were right.

What clinicians can use from this

For inlays and onlays, impression quality drives most of the outcome. A clear finish line, a cavity without unnecessary sharp internal angles, and a shade photograph taken before the tooth dehydrates all help the lab considerably. If the cavity is too shallow in a load-bearing area, raise it with the lab before production rather than at try-in.

See onlay, inlay and overlay, or contact our team about a specific case.

Written for dentists and technicians. Khai Nguyen Dental Lab manufactures to clinical prescription only and does not sell directly to patients.


WhatsApp